
Ember: An AI chatbot that helps people face breast cancer screening fear
This project explores whether an AI conversational agent informed by ACT-based psychological techniques can improve women’s willingness to undergo breast screening and reduce fear/anxiety towards it.
Compares an ACT-informed agent with an information-only agent across 24 participants.
Results show the ACT-informed agent increased willingness to attend screening and reduced fear/anxiety more than information alone. Rather than treating fear as something to correct, the research proposes an emotionally responsive approach to health chatbot design, showing how this could shape the design of future digital health tools.
What I did
UX research, Design lofi and hifi prototypes, Project management
Duration
7 months, Feb 2026 - Aug 2026
Tools
Claude Code, Figma, SPSS, NVivo
The Problem
The barriers to screening are psychological
Breast cancer was the leading cause of cancer-related death among women worldwide in 2024. The good news is that five-year net survival for breast cancer now exceeds 85%. The key is early detection and timely treatment.
However, in 2024/25, around 30% of eligible women in England didn't take up the offer of breast screening.
A big part of the reason is psychological: embarrassment, fear of a bad result, fear of discomfort during the screening, or simply feeling healthy enough not to bother.
Research Gaps
①
Focus on diagnosed women
Psychological interventions in breast cancer mainly support women already diagnosed.
②
Chatbots rely on CBT
Theory-informed chatbots for health behaviour change are mainly based on CBT.
③
ACT shows promise
A recent study suggests ACT can reduce stress and anxiety in breast cancer patients.
💥 the research gap
ACT-informed conversational agents for people who are not ill, but who avoid screening remain unexamined.
💭 So…what’s Acceptance and Commitment Therapy (ACT)?
ACT aims to increase psychological flexibility, the ability to follow one’s values rather than one’s anxiety (Hayes et al., 2006).
Aim and Research Questions
To investigate the role of ACT-informed psychological techniques in the design of an LLM-based chatbot for breast screening.
RQ1
Willingness
What is the effect of the chatbot on willingness to undergo breast screening?
RQ2
Fear and anxiety
What is the effect of the chatbot on fear and anxiety toward breast screening?
RQ3
Personality
What is the relationship between personality traits and changes in willingness and fear/anxiety?
Final Design
Ember: ACT-informed conversational agent
The system prompt for the ACT-informed CA (called Ember in the experiment) was built around four core ACT principles: acceptance, cognitive defusion, values clarification, and committed action. The information-only CA was instructed to give factual information only, such as how long the procedure takes, and not to respond to emotional questions.
Demo of each ACT principle
Acceptance
• Design principle
Meet the feeling plainly, without rushing to reframe or resolve it.
• Conversation example
User: I’m nervous about breast screening.
Ember: That nervousness makes complete sense, especially when so much of it is unknown.

Cognitive Defusion
• Design principle
Offer catastrophic thoughts as thoughts rather than facts.
• Conversation example
User: I’m afraid they’re going to find something bad.
Ember: That fear is real. But notice it’s a thought your mind is
giving you, not a fact you know yet.

Values Clarification
• Design principle
Connect screening to what the participant already cares
about.
• Conversation example
User: I just want to enjoy quality time with my family.
Ember: Going for screening can be one way of protecting
exactly that.

Committed Action
• Design principle
Close with one small, concrete step that translates intention into behaviour.
• Conversation example
Ember: Would you be willing to look at the NHS screening page this week?


Study Design
Compared Ember with an information-only chatbot to see if emotional support made a difference
Every participant talked to two conversational agents about breast screening.
Ember, one of the two agents, acknowledged how participants felt. The other gave factual information only (information-only CA).
Half talked to Ember first, half talked to the other agent first, to make sure the comparison between them was fair.
• Experiment Procedure
It was a single-session experiment lasting approximately 35 to 50 minutes

Iteration
Evaluation made the conversations better suited to breast screening, and safer
The system prompt went through 6 iterations, informed by:
①
Heuristic evaluation
• Information-only CA was revised to follow participants’ own questions rather than delivering information in a set order • Safety lock added: conversation ends once a crisis message is triggered

System prompt and UI iterations
②
Expert review
• Conversation flow slowed down, with more turns per process • Safety notice added to the welcome screen (right to withdraw at any time )


③
Pilot testing
Agent was instructed to proceed with values clarification and committed action even without expressed fear or anxiety
before
users didn't express any fear or anxiety
only provide information
after
users didn't express any fear or anxiety
guide them to values clarification and committed action
Data Collection
Quantitative data were collected using the measures below:

After both conversations, I collected qualitative data through interviews, asking participants how they felt, what they thought, and whether they had any problems using the agents.


Data Analysis
I analysed the quantitative data in SPSS and the qualitative data in NVivo using thematic analysis.

Results
The ACT-informed CA reduced fear more than information alone
RQ1 Willingness
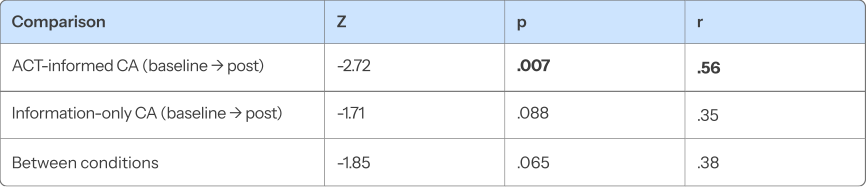
The ACT-informed CA significantly increased willingness to attend breast screening, while the advantage of the ACT-informed CA over information alone could not be confirmed.
I feel like it made me more interested and more motivated to do it. So that would make me actually do it. -P14
RQ2 Fear and anxiety
Both CAs reduced fear, but the reduction was significantly larger after the ACT-informed CA.
It told me it was normal to feel anxious in this situation, and felt I was accepted. -P18
It asked me what’s the priorities in my life, and told me I can look at these things through a health perspective. -P12

RQ3 Personality
The results demonstrated that there was no relationship between personality traits (Mini-IPIP) and changes in willingness and fear/anxiety to undergo breast screening, with all p>.05. This indicates that personality traits could not explain how participants responded to the ACT-informed CA.
Exploratory analysis
①
Participants with higher baseline fear showed larger fear reductions after the ACT-informed CA (rho = -.63, p < .001)

②
The association between order and fear rebound was statistically significant, p=.037, with a large effect size (Cramér’s V=.513) → This suggests that although fear was reduced after the first conversation, the reduction might not be maintained when the second conversation provided information alone.

I could just picture my breast, and then just like compression. So that worried me a bit more, I can’t lie. -P11
Key Findings
①
What ACT-informed CA offered beyond information
Participants felt their anxiety was accepted rather than dismissed, and the ACT informed CA helped them connect screening to what already mattered in their lives.
Design Implication

Apply ACT principles in the dialogue
・Recognise and accept users’ emotions instead of denying or correcting them and avoid reassuring users without understanding the context ・Ask about values and link them back to the screening context
②
Information reduced fear but also created it
The information-only agent helped by answering “what will happen”, but when it mentioned something like pain and then moved on, it left some participants more worried than before.
Design Implication
Follow information with emotional response
When content may raise concerns related to discomfort (e.g. pain), respond to the emotion it creates, not only facts
③
Participants with higher baseline fear benefited most
Participants with higher baseline fear saw a bigger drop in fear when talking to the ACT-informed CA. But feeling less afraid didn’t always mean they were more willing to attend.
Design Implication
Assess baseline fear and adapt the conversation
・High-fear users: accept their worries before introducing information ・Low-fear users: provide information sooner and offer ACT support if needed
④
Order as a design variable, not only a methodological control
When the information-only agent came second, some participants’ fear went back up. This suggests that the order in which agents are used isn’t just a research design choice, it’s something designers need to think about.
Reflections
This was one of the most challenging research projects I've done so far. Digital healthcare is a complicated field, so this project required lots of iteration including collaboration with a therapist, to refine the AI.
The biggest takeaway was how much I learned by actually listening to users. It was only through the combination of interviews and quantitative data that I found out information alone is not neutral, and that it can also trigger anxiety or fear. Giving people the right information is only half the job. What happens after you give it matters just as much.
Curious about my work, or have suggestions to share?
I’d love to hear from you, let’s connect!

